Occipito-Podal Reflexotherapy and the Viscera of the Abdominal and Pelvic Cavities
The nervous system, the viscera, and stress — a clinical perspective in Occipito-Podal Reflexotherapy



Atlas of the third book
More than 400 illustrations connecting anatomy, physiology and manual therapy techniques.
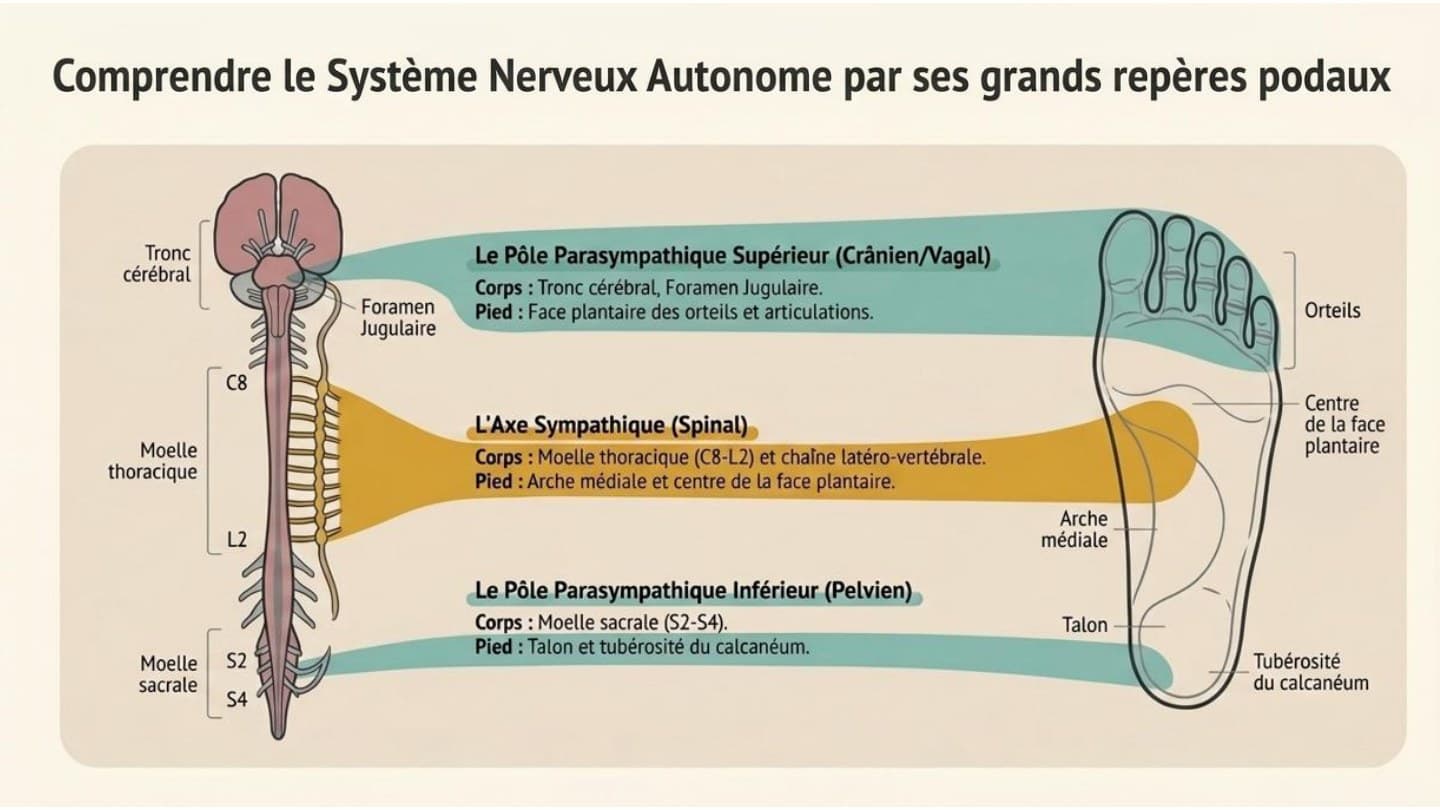
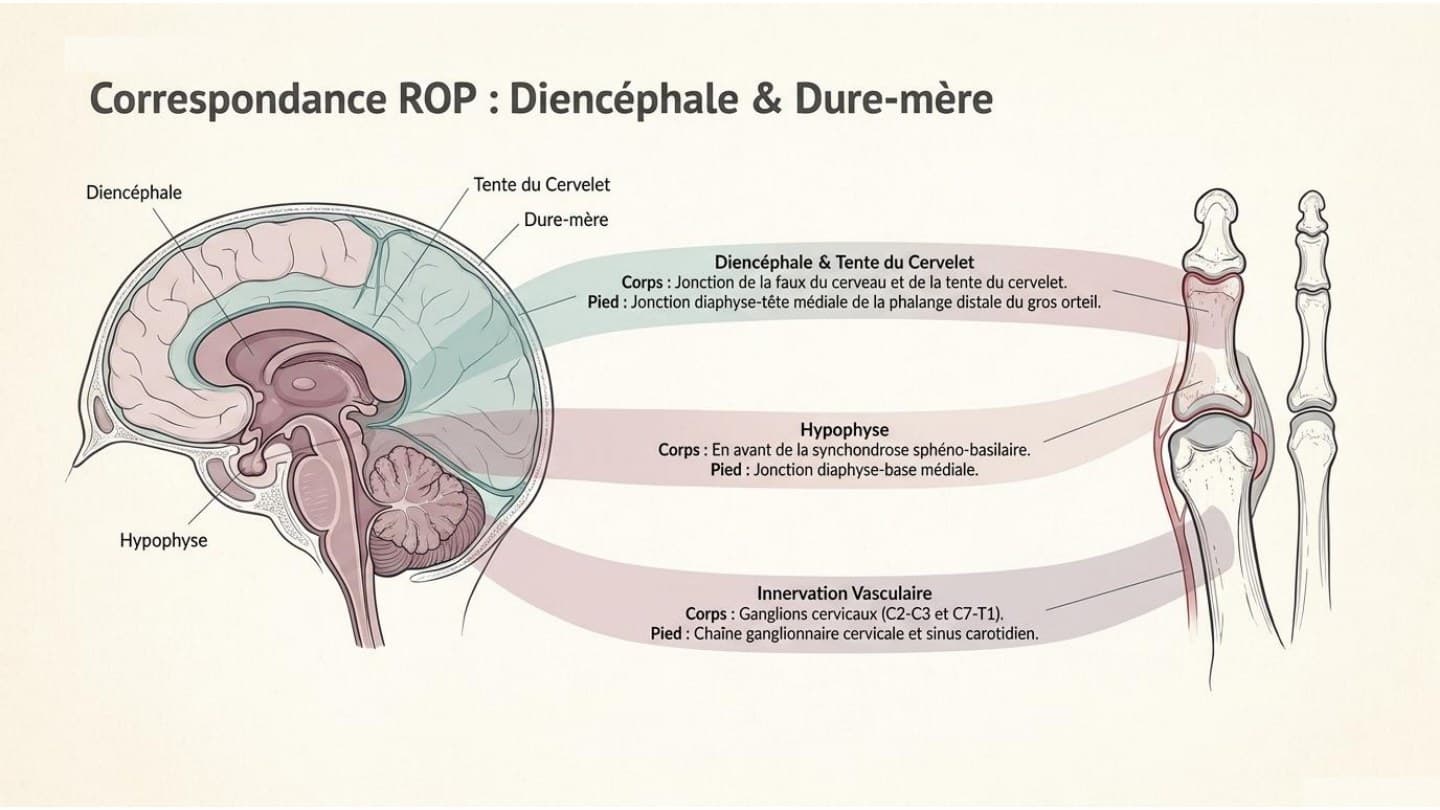
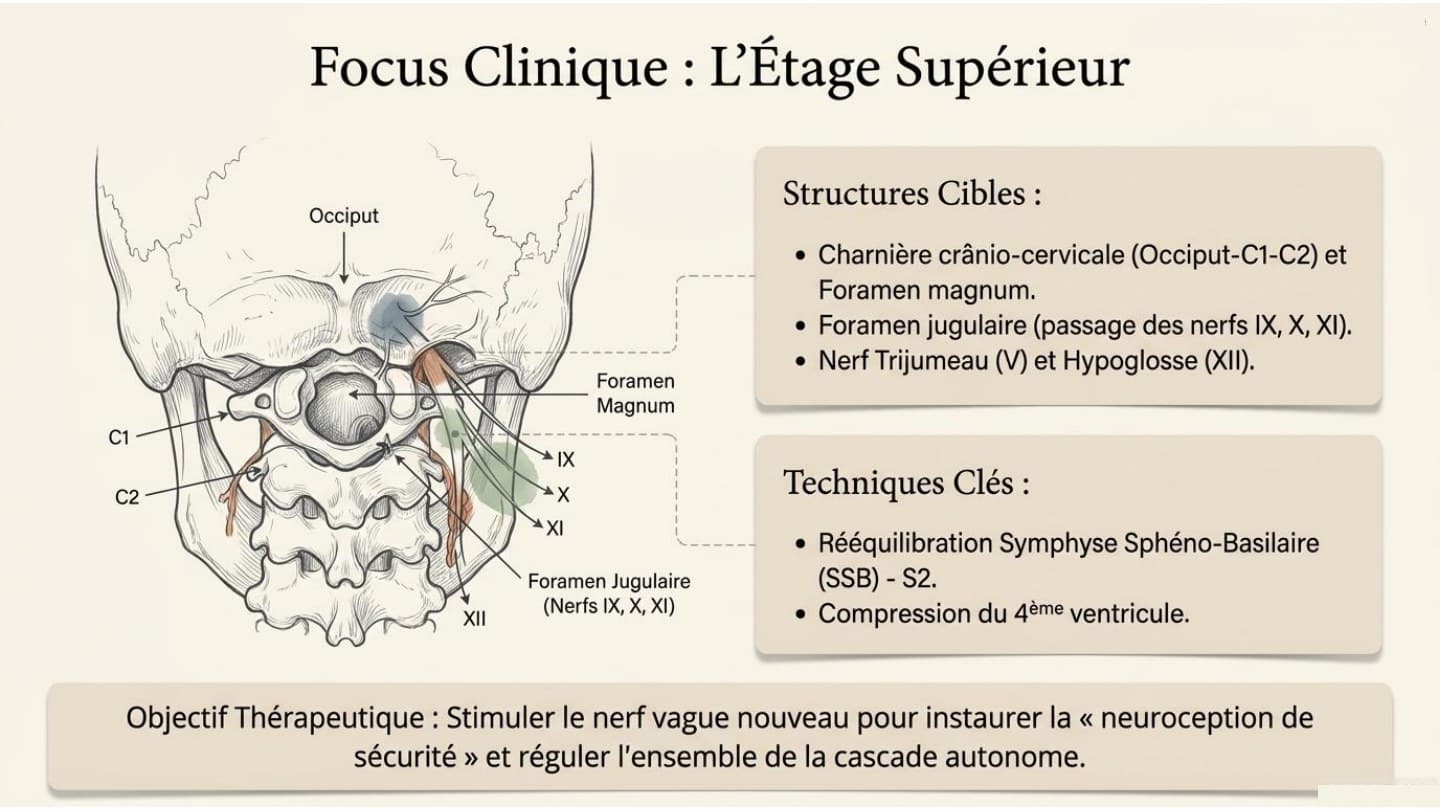
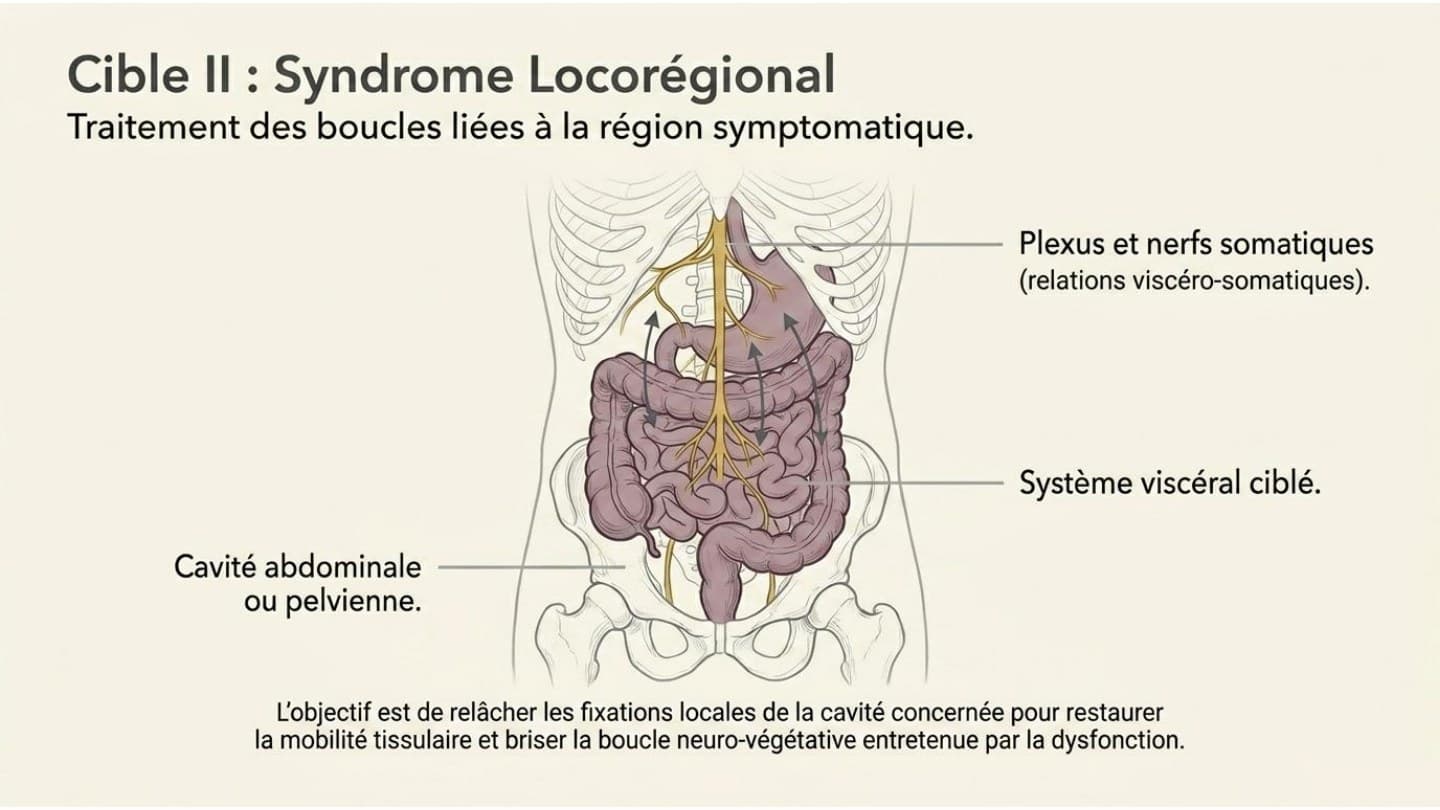
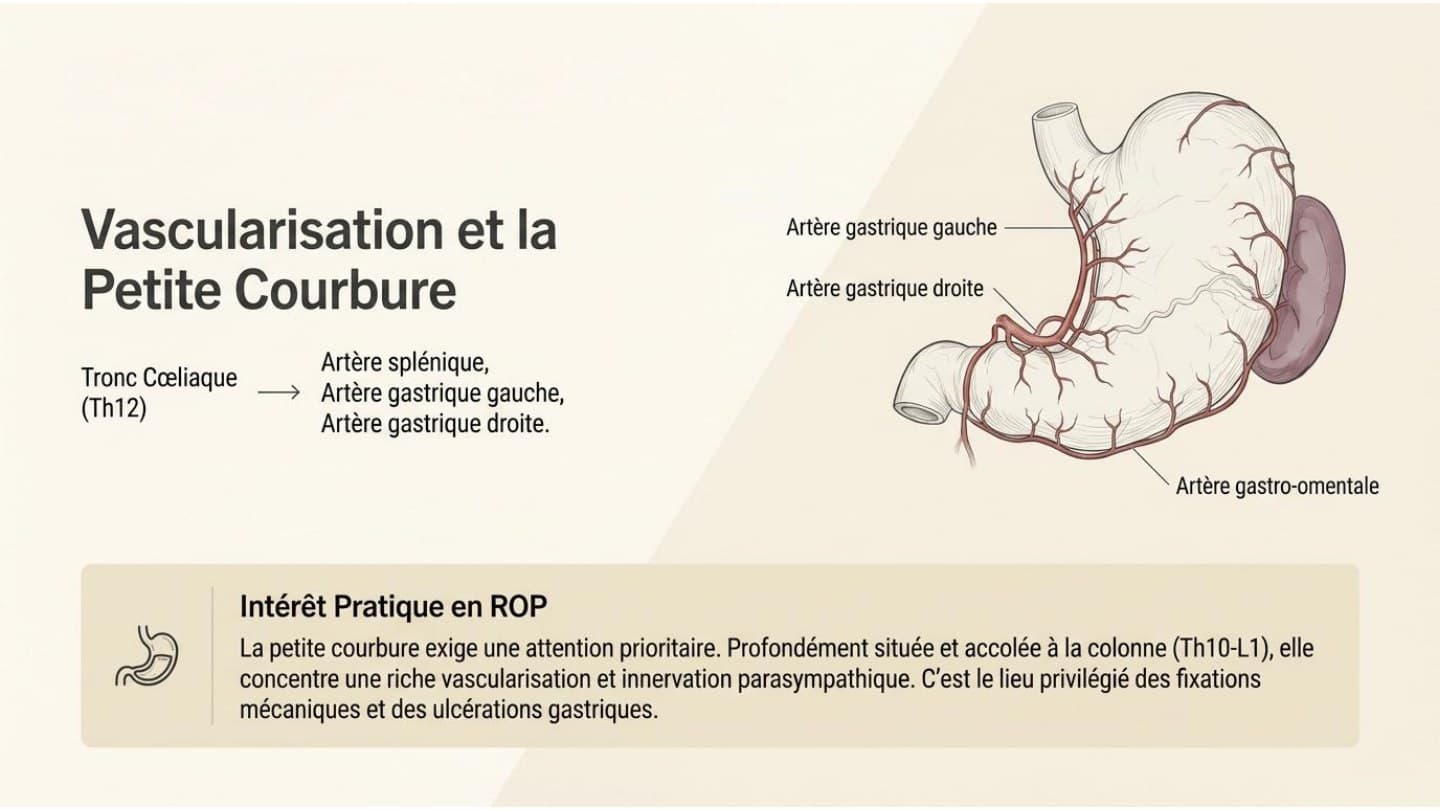
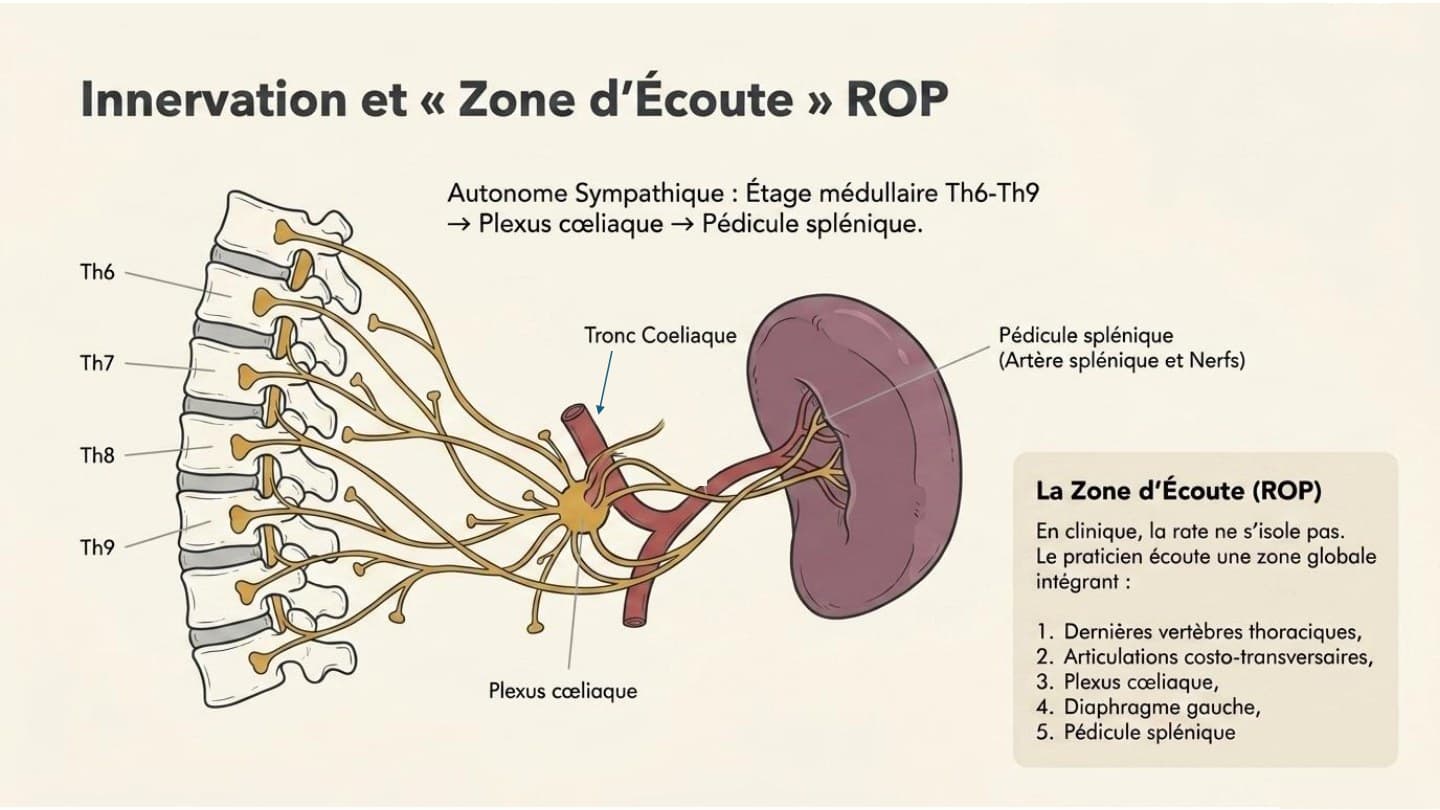
A selection of plates from the chapters offers a preview of the book’s illustrations: reflex maps, anatomical diagrams, clinical summaries and treatment landmarks.
A preview of the book’s maps, diagrams and summaries, designed for mobile viewing.
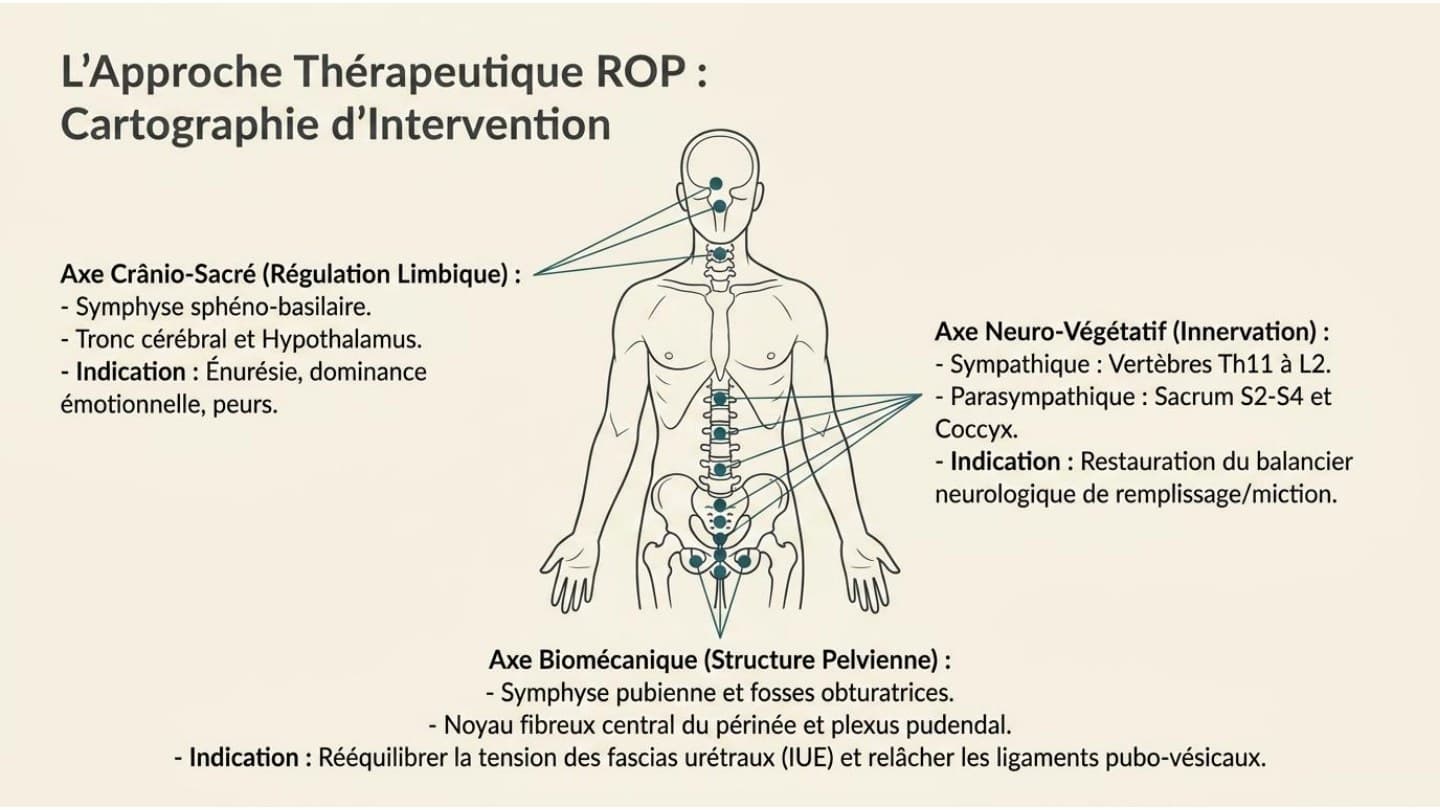
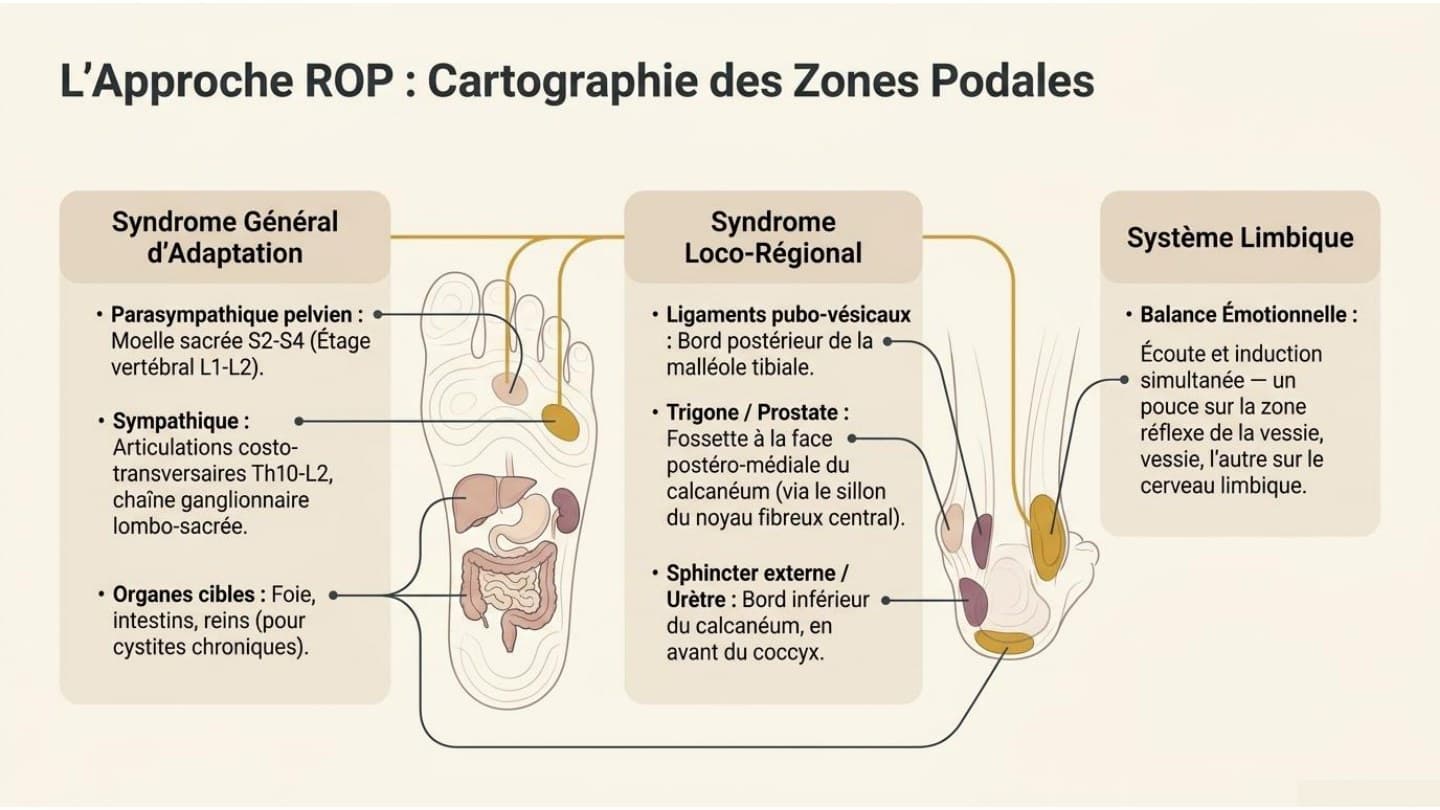
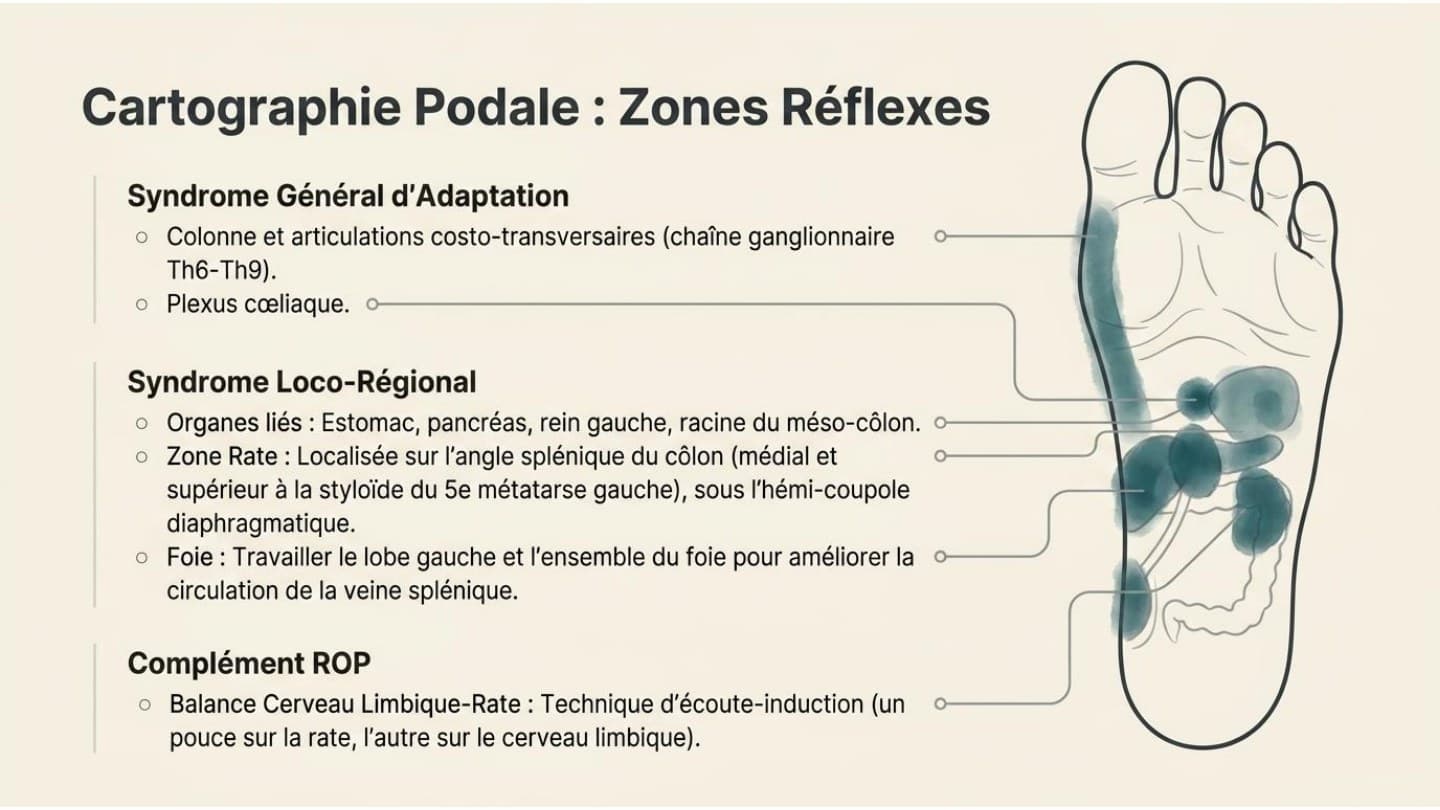



Guy Boitout
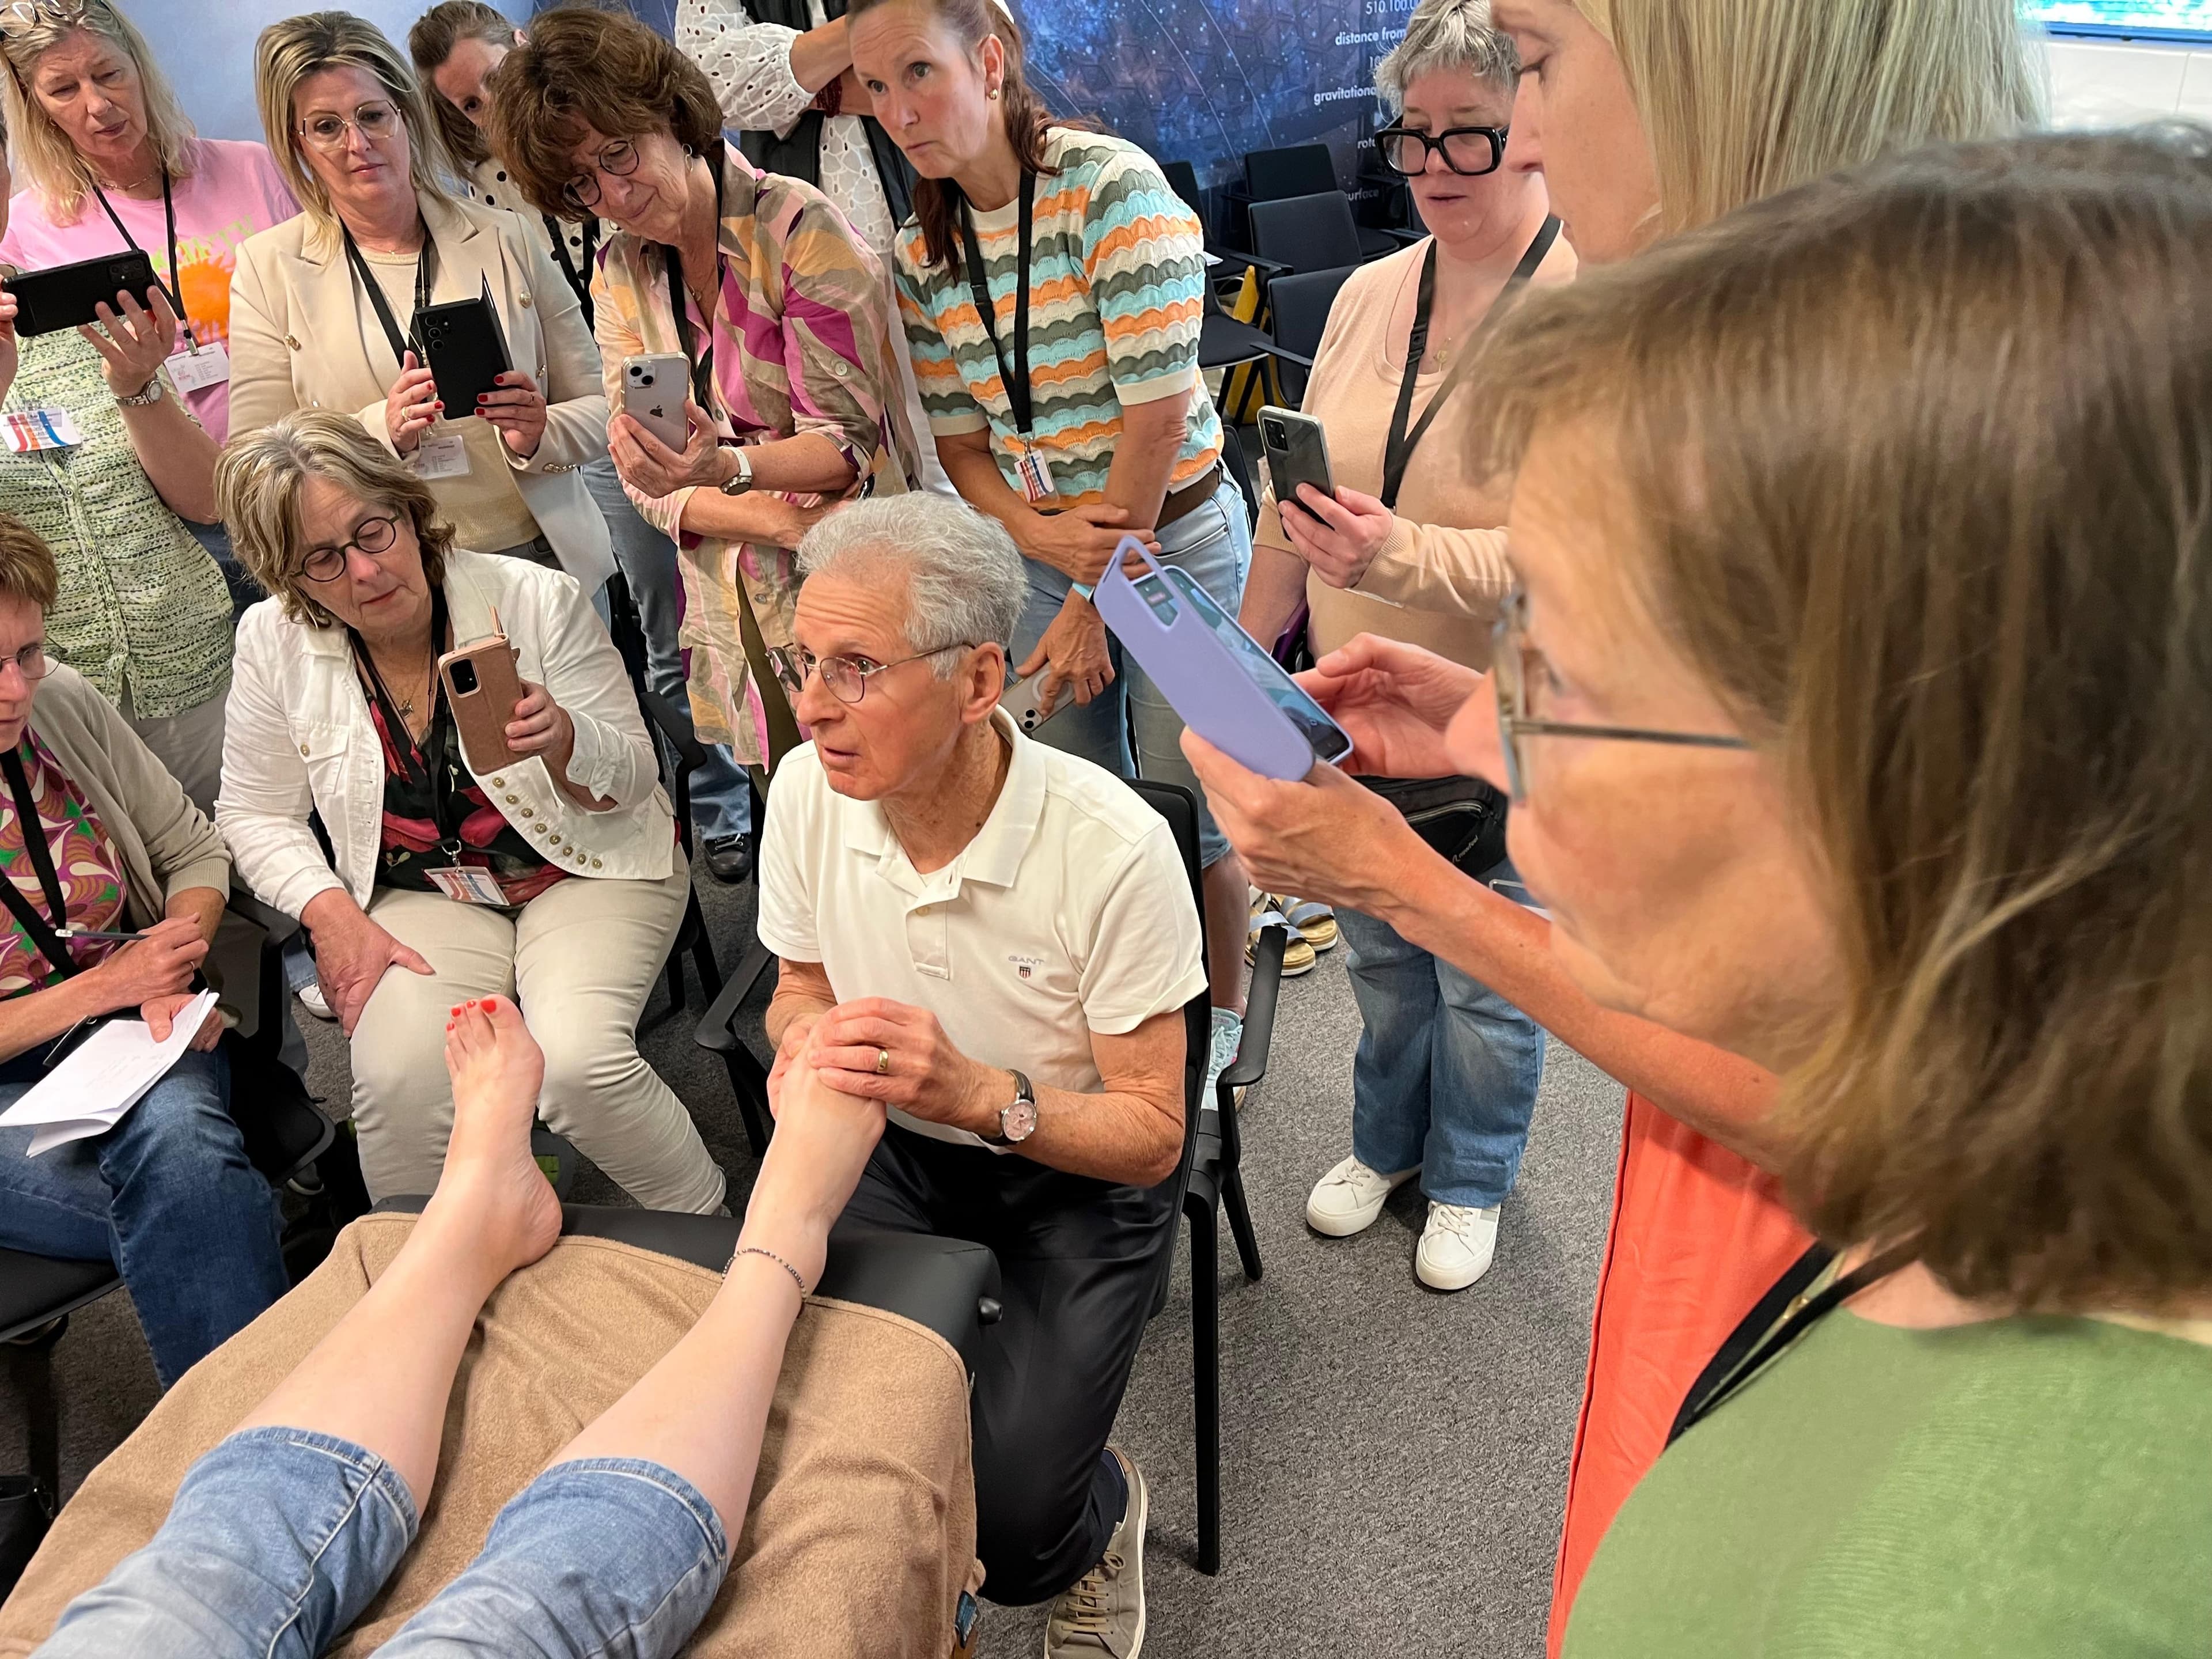
Guy Boitout is the founder of Occipito-Podal Reflexotherapy (R.O.P.), a massage technique based on a three-dimensional representation of the body on the foot and the occiput. For more than fifty years, he has taught and developed this approach through the R.O.P. Training Institute, based in Sully-sur-Loire, France.
Originally trained as a physiotherapist, he discovered reflexotherapy — through the Ingham method — in 1978, and later visceral osteopathy with Jean-Pierre Barral. These two decisive influences led him, together with Jean-Pierre Vadala, to develop the original three-dimensional R.O.P. reflex mapping. His first two books were published by Elsevier Masson; this third and final volume is self-published.
His training programmes are accredited for continuing professional development (registration number 24450434645, Prefecture of Centre–Val de Loire) and are designed for reflexotherapists, osteopaths, physiotherapists, and other healthcare professionals.
A fifty-year journey
This third volume continues to explore what makes Occipito-Podal Reflexotherapy unique: a comprehensive three-dimensional representation of the body, in the form of a baby in the foetal position, within the feet; occipital reflex zones; and a constant reference to anatomy and physiology.
After a first book dedicated to the musculoskeletal system and a second focused on the spinal and cranial somatic nerves, this volume addresses the autonomic nervous system, stress mechanisms, and the abdominal viscera — the hidden core of the body's regulation.
“It could not have been otherwise in reflexotherapy. As in visceral osteopathy, the autonomic nervous system is at the heart of everything: it governs, regulates and restores — and it is what R.O.P. seeks to reach as a priority.”— Guy Boitout · Preface to the third book
The foot is a sensory entry point to the nervous system.
Pressure on the sole stimulates sensors in the skin. Their signals travel through sensory nerves to the spinal cord and brain. How could this information modify a visceral function? Five neuroanatomical bridges help us follow the reasoning, step by step.
The pelvic region, particularly the bladder, provides a promising starting point for this research. Our guide explains the anatomy, the effects already measured and what remains to be tested for manual R.O.P. techniques. The full scientific article then explores each bridge in greater depth.
Understand the five bridges →by Elsevier Masson
online and in print
R.O.P. Journey
photos, plates & reflex maps
A step-by-step learning journey
From the personal preface to the urogenital organs of the pelvis, the book follows a logical progression through five major parts. Each layer builds on the previous one, giving practitioners a complete, practical clinical understanding.
640Wealth of illustrations
Select a chapter to preview its contents.
Introduction
Origins of the method, clinical principles and the R.O.P. protocol.
3 chaptersIn the author's own voice: from physiotherapy to reflexotherapy through the Ingham method in 1978, then to visceral osteopathy with J.-P. Barral, and finally to the development of R.O.P. with Jean-Pierre Vadala. The DNA of the method, presented in a few concise and personal pages.
A mechanical and neurophysiological framework for practitioners: mobility versus motility; the four drivers of visceral movement — somatic, autonomic, intrinsic motility, and biorhythms; turgor; intracavitary pressure; and serous membrane gliding.
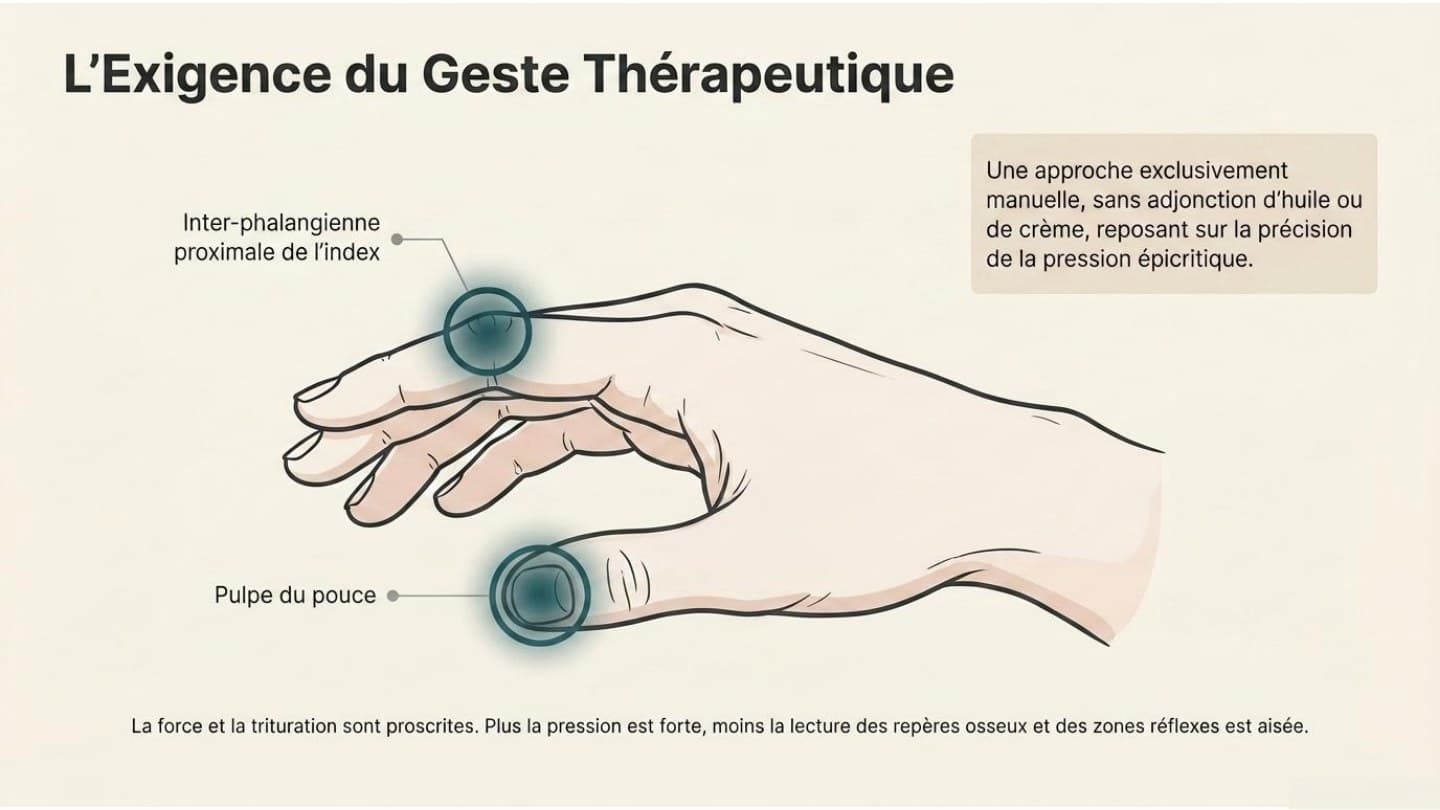
The complete clinical protocol: manual technique using the thumb pad, pressure adjusted to tissue texture (the “drumskin” feel), the three phases of a session, and a hierarchical treatment sequence — general syndrome → locoregional → limbic — grounded in neurophysiology.
Nervous Systems
CNS (brainstem, limbic system, neurotransmitters) and ANS (sympathetic, parasympathetic, vagus nerve).
2 chaptersFrom MacLean's triune brain model to the reticular formation: brainstem, cerebellum, limbic system, cortex, basal ganglia, and neurotransmitters. Foot and occipital reflex zones corresponding to each cerebral structure.
Parasympathetic and sympathetic systems: functions, homeostasis, the ANS–sleep relationship, and the enteric nervous system. The vagus nerve — with 70 to 80% afferent sensory fibres — and its anti-inflammatory role. A clinical framework for autonomic imbalances in R.O.P.
Stress & Regulation
Stress mechanisms, polyvagal theory, and autonomic regulation.
2 chaptersFrom Walter Cannon's concept of homeostasis to Hans Selye's general adaptation syndrome: distress, eustress, and physical, biochemical, and emotional stressors. The central role of the ANS and the limbic system — and the place of R.O.P. interventions.
Dr. Stephen Porges: three phylogenetic levels of the ANS — immobilisation, or old vagal; mobilisation, or sympathetic; and social engagement, or new vagal. Clinical implications for vagal regulation in R.O.P.
Abdominal Viscera
Cavities, diaphragm, digestive tract, accessory glands, and colon — anatomy and R.O.P. mapping.
9 chaptersComplete architecture of the abdominal cavity: the peritoneum; intra-, retro-, and subperitoneal spaces; fasciae; and mesenteries. The influence of thoracic pressure changes on the viscera. An R.O.P. clinical interpretation of fascial and mechanical constraints.
The diaphragm as a respiratory motor — approximately 16 breaths per minute and tens of thousands of cycles per 24 hours — with visceral and venolymphatic functions. Diaphragmatic attachments, the oesophageal hiatus, pressure gradients, and venous return. Clinical applications in R.O.P.
Complete anatomy of the stomach — J shape, four segments, lower oesophageal sphincter, cardia, fundus, and pylorus — the physiology of digestion in an acidic environment, the impact of stress on gastric secretion, and the emotional dimension of the organ in R.O.P.
The U-shaped duodenum — approximately 25 cm long — with four segments, D1 to D4; duodenal papillae; the sphincter of Oddi; and the biliopancreatic junction. Aortomesenteric compression, the impact of stress on the mucosa, and the R.O.P. protocol for duodenal motility.
The largest viscus — 2% of body weight yet 25% of cardiac output. Digestive, metabolic, immune, and detoxifying functions; the Glisson capsule, diaphragmatic ligamentous attachments, the portal triad, and the intra- and extra-hepatic biliary tract. R.O.P. clinical interpretation of hepatic mobility.
A mixed gland — exocrine (1.5 to 2 L of pancreatic juice per day) and endocrine (insulin, glucagon, somatostatin). Retroperitoneal, wrapped around L2–L3, with its head set within the duodenal frame. Wirsung and Santorini ducts, vulnerability to abdominal trauma, and the R.O.P. approach to pancreatic motility.
A lymphoid organ served by blood rather than lymph — white pulp (immunity) and red pulp (destruction of worn-out red blood cells). Subdiaphragmatic on the left, intraperitoneal, mobile with diaphragmatic excursions. Phagocytosis, haematopoiesis, and immune defence — with foot and occipital reflex zones in R.O.P.
Anatomy of the jejunum–ileum and mesentery through an R.O.P. clinical interpretation: the mesenteric root as a highly reflexogenic zone, nutcracker syndrome, the gut–brain axis, and the microbiota–immunity relationship. Reflex mapping included.
A colonic frame of about 1.50 m from the ileocaecal junction to the rectum: caecum, ascending, transverse, descending, and sigmoid colon. Haustrations, taeniae coli, and omental appendages; reabsorption of fluids and formation of stool. R.O.P. clinical interpretation of colonic motility and the hepatic and splenic flexures.
Urogenital & Pelvic
Kidneys, pelvic cavity, bladder, reproductive organs, and erectile system — anatomy and R.O.P. approach.
6 chaptersBean-shaped retroperitoneal kidneys in the lumbar fossae, capped by the adrenal glands. Renal compartment (anterior and posterior fascial layers), relationships with the liver, spleen, colon, and Toldt's fascia. Homeostatic functions and vulnerability to collision trauma — with a dedicated R.O.P. protocol.
The space between the pelvic inlet and outlet — genital and urinary systems functionally intertwined. Sagittal and transverse septa defining a medial visceral compartment and lateral compartments, the inferior hypogastric plexus, and autonomic innervation. R.O.P. clinical interpretation of pelvic–visceral interactions.
Urinary reservoir behind the pubis, with a mobile dome and a base anchored to the pelvic floor. Detrusor (three layers of smooth muscle fibres), pubovesical ligaments, hormonal dependence. Stress incontinence, cystitis, and disorders of pelvic support — the R.O.P. approach to bladder dynamics.
Uterus, vagina, ovaries, and fallopian tubes — the female reproductive system and its hormonal landscape. Pelvic statics, myometrium and endometrium, uterine malpositions, and dysfunctions often hidden behind low-back pain, sciatica, dysmenorrhoea, or dyspareunia. A distal, respectful, and comprehensive R.O.P. approach.
Testes, epididymides, vas deferens, seminal vesicles, prostate, urethra, and penis. Embryonic migration of the gonads, prostatic enlargement around the age of sixty and its urinary, sexual, and psycho-emotional impact. A distal R.O.P. clinical interpretation — non-iatrogenic and respectful of personal privacy.
Symmetrical anatomy of the erectile organs: corpora cavernosa, corpus spongiosum, and vestibular bulbs; ischiocavernosus and bulbospongiosus muscles; Bartholin's and Cowper's glands. The urogenital triangle of the perineum — a common anatomical foundation for arousal, erection, lubrication, and ejaculation. R.O.P. contributions.
The R.O.P. Clinical Protocol in Detail
- Meissner's corpuscles — fine tactile sensitivity to light pressure, especially in glabrous skin.
- Merkel discs — gentle static pressure, located at the base of the epidermis.
- These fast-conducting afferents may modulate nociceptive transmission through the gate control model, helping to explain the analgesic effect of R.O.P.
First address the overall clinical context, then the symptomatic area and, if needed, the limbic component.
- Pressing hard to “feel” — fine tissue reading is lost.
- Seeking pain as proof of efficacy — an overdosing artefact.
- Treating the same zone too long — short stimulations, re-evaluated each time.
A Clinical Manual, Not a Theoretical Treatise
Every concept is grounded in references to classical anatomy, neurophysiology, and visceral osteopathy. These solid foundations support clinical adaptation.
Original diagrams integrate the three-dimensional representation of the body, in the foetal position, within the feet and occipital reflex zones. Each organ is supported by dedicated visual material.
From textural diagnosis to hierarchical treatment, each visceral chapter concludes with practical guidance that can be applied directly in a session.
The Author's Voice
"Visceral mobility is made possible by four main drivers: the somatic nervous system, the autonomic nervous system, intrinsic motility, and biorhythms. Their interaction defines the practitioner's clinical context."
Chapter 1 — General PrinciplesThree chapters
free to read
The introduction, the chapter on the R.O.P. treatment protocol and the chapter on the small intestine are freely available — to discover the educational rigour and clinical depth of this work.
Read online, with illustrations. A single registration gives access to all three complete chapters, with no PDF sent.
Introduction · Chapter 2 · Chapter 14Online Book or the complete package
Two formats are available: the enriched online book (extra illustrations, review sheets, interactive visuals, self-assessment quizzes), or the online book together with the printed edition.
Before you order
Start with the 3 free chapters
No credit card · Immediate access
Start reading for free →Enriched digital edition: extra illustrations, review sheets, interactive visuals, and self-assessment quizzes.
- Extra Illustrations
- Review Sheets
- Interactive Visuals
- Self-Assessment Quizzes
- Immediate Access · Permanent
The complete package: full enriched online book plus the printed edition shipped to your address.
- Online Book Included (enriched)
- Printed Copy Included
- Immediate Online Access
- Printed Copy Shipped
- Both Formats in a Single Order
Coming soon
Be notified as soon as the book is released
Occipito-Podal Reflexotherapy and the Viscera of the Abdominal and Pelvic Cavities
The complete book — online and in print — is in preparation. Leave your email address to be notified as soon as it is released.